

























Why Is BET Incubated at 37°C for 60 Minutes?
If you’ve worked anywhere near a pharmaceutical QC lab, you’ve likely watched a technician set a rack of reaction tubes into a water bath, note the time, and walk away for exactly one hour. That step incubating Bacterial Endotoxins Test (BET) reaction tubes at 37°C ± 1°C for 60 ± 2 minutes looks almost too simple to matter. But the temperature and the timer are doing real analytical work, and getting either one wrong can quietly invalidate a result.
Here’s what’s actually happening during that hour, and why the specifications are as tight as they are.
What the Bacterial Endotoxins Test Is Measuring
The Bacterial Endotoxins Test relies on Limulus Amebocyte Lysate (LAL), a reagent derived from horseshoe crab blood. LAL contains enzymes that respond specifically to bacterial endotoxins the lipopolysaccharides (LPS) found in the outer membrane of Gram-negative bacteria. When LAL meets endotoxin under the right conditions, it triggers an enzymatic cascade that ends in a visible or measurable change: in the gel-clot method, a firm gel forms at the bottom of the tube.
That enzymatic cascade is the whole test. Everything about the incubation step exists to let that cascade run cleanly, once, under conditions everyone can reproduce.
Why 37°C: Matching the Enzyme’s Optimal Zone
LAL’s clotting enzymes don’t work at a fixed rate regardless of temperature like most enzymes, their activity peaks in a specific range. 37°C sits at that peak for the LAL cascade, which is also, not coincidentally, human body temperature. Running the reaction at this temperature means the enzymes are working as efficiently and predictably as they’re capable of, rather than sluggishly (too cold) or unstably (too hot).
There’s a secondary benefit here too: because 37°C mirrors physiological conditions, the test result better reflects how endotoxin would actually behave and be recognized inside the human body relevant given that a positive BET result is standing in for a pyrogenic risk to a patient.
Why 60 ± 2 Minutes: Letting the Reaction Finish, Without Overshooting
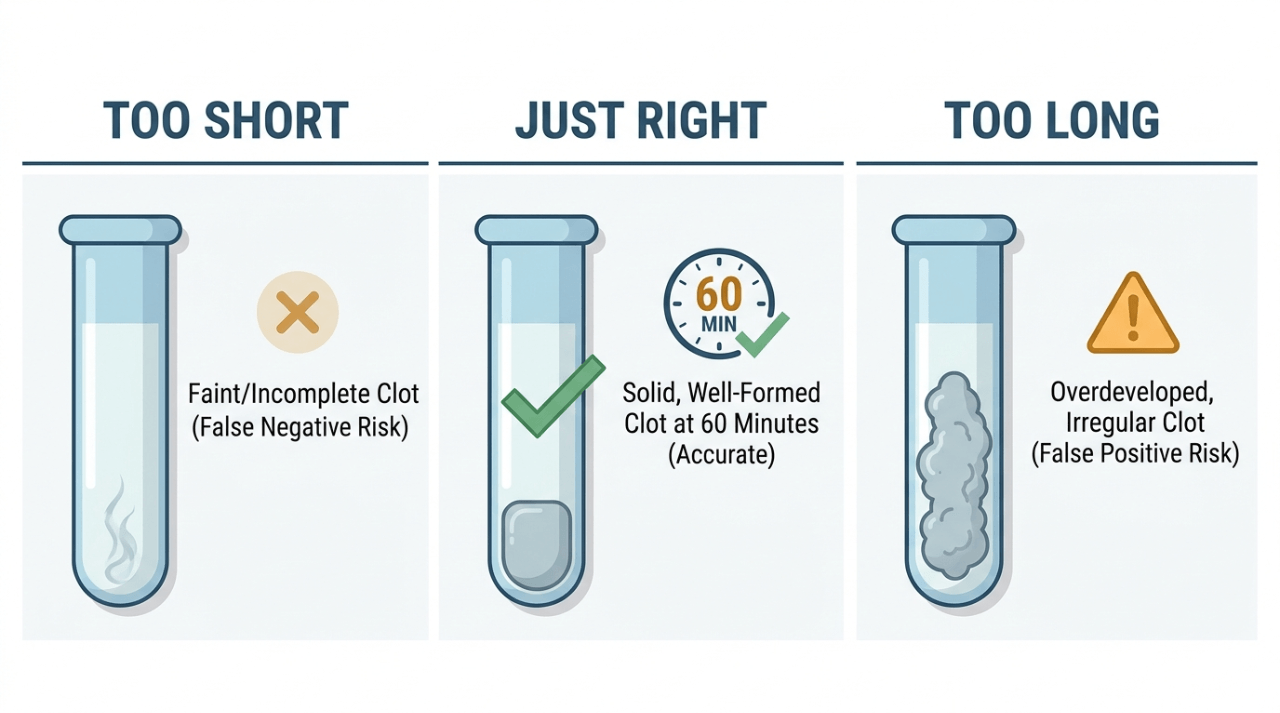
Enzymatic reactions need time to reach completion, and the gel-clot reaction is no exception. The one-hour window is calibrated to be long enough that the reaction fully develops so a genuinely endotoxin-containing sample reliably produces a detectable clot without running so long that the system starts to break down or the reaction “overdevelops” in ways that could distort the reading.
This is a narrower needle to thread than it looks:
- Too short, and the reaction hasn’t finished. A sample that does contain endotoxin might not yet show a firm clot, producing a false negative.
- Too long, and you risk overdevelopment changes to the gel or reaction matrix that no longer reflect a clean, standardized endpoint.
The ± 2 minute tolerance exists precisely to keep every run inside that window, whether it’s the first tube pulled or the last.
Read More: Why Is Sterility Test Incubation 14 Days? (Not More, Not Less)
Standardization: Making Results Comparable Across Runs
Pharmaceutical testing lives or dies on reproducibility. If every lab or every technician used a slightly different incubation time or temperature, a “positive” in one run might not mean the same thing as a “positive” in another. Fixing both variables tightly (37°C ± 1, 60 ± 2 minutes) means that when a gel-clot forms or fails to form, that outcome can be attributed to the presence or absence of endotoxin not to incubation drift.
This also protects test integrity across the reagent’s shelf life and across different instruments (water baths vs. dry heating blocks), since both are expected to hold the same tolerances.
Where These Limits Actually Matter: Regulatory Context
The gel-clot BET procedure mix equal parts sample and LAL reagent, incubate at 37°C for 60 minutes, then invert the tube to check for a stable clot is described consistently across pharmacopeial and industry sources, which is part of why it has held up as a validated method for decades.
The endotoxin limits that BET is used to confirm vary depending on what’s being tested:
- Water for Injection (WFI): the U.S. Pharmacopeia (USP) sets an endotoxin limit of 0.25 EU/mL.
- Water for hemodialysis: under the ANSI/AAMI/ISO 23500 series (and its identical Indian counterpart, IS 17646, Part 3), dialysis water must contain less than 0.25 EU/mL of endotoxin a limit that matters enormously given that dialysis patients are exposed to large volumes of this water directly through their bloodstream.
The U.S. FDA recognizes BET as its accepted method for endotoxin detection precisely because of this combination of sensitivity and reproducibility, and the Indian Pharmacopoeia similarly endorses the test for pyrogen-free assurance in pharmaceutical products.
FAQ
Why can’t BET be incubated at a different temperature, like room temperature?
Because LAL’s enzymatic activity is temperature-dependent and peaks around 37°C. At lower temperatures, the reaction is slower and less predictable, which undermines the standardization the test depends on.
What happens if incubation runs longer than 62 minutes?
It falls outside the validated tolerance window. Depending on lab SOPs, this can require the run to be repeated, since overdevelopment can distort whether a clot reading is genuinely valid.
Is the gel-clot method the only BET method that uses this incubation step?
No gel-clot is the original and simplest LAL method, but kinetic turbidimetric and kinetic chromogenic methods also incubate at 37°C, though they measure the reaction continuously (via turbidity or color change) rather than checking a single endpoint.
Why does dialysis water have the same 0.25 EU/mL limit as Water for Injection?
Both represent direct or near-direct blood contact scenarios, which is why regulators hold them to comparably strict endotoxin limits, even though they’re governed by different standards (USP for WFI, ISO 23500/IS 17646 for dialysis water).
Who actually enforces these incubation and limit specifications?
Pharmacopeial bodies (USP, Indian Pharmacopoeia, European and Japanese Pharmacopoeias) publish the test chapters, and regulators like the US FDA audit pharmaceutical manufacturers against them during inspections.


